The Fate of Delusions: Why Some Disappear, Some Persist, and Others Transform
 Understanding the evolution, resolution and psychological aftermath of delusional beliefs.
Introduction: What Happens to a Delusion After Treatment?
A patient develops an unshakeable belief that colleagues are secretly monitoring his activities.
Every conversation appears suspicious. Ordinary events acquire extraordinary meanings. Even reassuring explanations become part of the perceived conspiracy.
Following psychiatric treatment, his sleep improves, anxiety decreases, and he resumes his everyday activities.
But when asked whether his colleagues were genuinely monitoring him, he responds:
“I don’t think about it anymore. But I still believe something was happening.”
Has his delusion disappeared?
Has he recovered?
Or has the delusion simply become less important to his life?
This is one of the most fascinating questions in clinical psychopathology.
Psychiatry traditionally devotes considerable attention to the origin, content and treatment of delusions. However, their longitudinal evolution deserves equal attention.
The fate of a delusion is not always its disappearance. It may lose emotional significance, become less convincing, remain isolated from everyday functioning, transform in content, or re-emerge during a subsequent episode.
Understanding these possibilities helps clinicians distinguish symptomatic improvement from genuine belief revision, while recognising that meaningful functional recovery can occur even when some abnormal beliefs persist.
1. Are Delusions Really Fixed Beliefs?
Delusions have conventionally been described as beliefs held with extraordinary conviction despite compelling contradictory evidence.
This description is clinically useful, but it can create the impression that delusions are permanently unchanging.
Research suggests otherwise.
A landmark longitudinal study by Appelbaum and colleagues, published in Comprehensive Psychiatry in 2004, followed hospitalised psychiatric patients over one year.
Among patients assessed repeatedly, substantial changes occurred in both the persistence and the content of delusions.
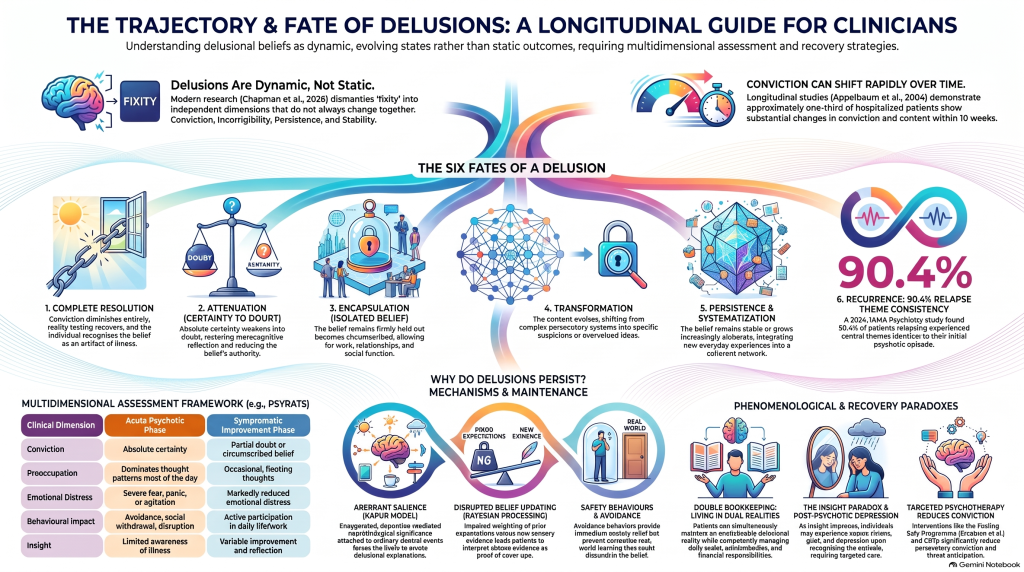
Approximately one-third of those experiencing delusions at a given assessment were no longer delusional ten weeks later.
The study did not establish that these individuals had recovered permanently. Rather, it demonstrated that delusions can change over comparatively short periods.
A 2026 review in Nature Mental Health, titled On the Fixed Nature of Delusions, further questioned the usefulness of treating fixity as a single characteristic.
The authors proposed distinguishing four properties:
- Conviction: How strongly is the belief held?
- Incorrigibility: How resistant is it to contradictory evidence?
- Persistence: How long does the belief continue?
- Stability: How much does its content change over time?
These dimensions need not evolve together.
A patient may remain convinced of a belief while becoming substantially less preoccupied by it. Another may retain persecutory fears but change their explanation for who is responsible.
Thus, the clinical course of a delusion cannot always be represented by a simple distinction between present and absent.
2. The Six Possible Fates of a Delusion
Classical psychopathology and contemporary longitudinal research suggest several recognisable patterns of change.
These are descriptive clinical patterns rather than formally validated stages of recovery. They may overlap, coexist, or occur in different sequences.
Fate 1: Complete Resolution
Some delusions disappear with treatment or resolution of the underlying episode.
A patient who previously believed that television presenters were communicating secret messages may later recognise that these experiences occurred during a period of illness.
Reality testing improves, conviction diminishes, and the patient no longer accepts the delusional explanation.
This can occur following treatment of schizophrenia-spectrum psychosis, mood episodes with psychotic features, and certain medical or substance-related conditions.
The prognosis depends substantially on the underlying disorder.
For example, delusions occurring during delirium may resolve when the medical disturbance is corrected, whereas delusions associated with a chronic psychotic disorder may require continuing treatment.
Importantly, remembering a former delusion does not mean that the delusion is still present.
A person may recall having believed something without continuing to believe it.
Fate 2: Attenuation — When Certainty Becomes Doubt
A second outcome involves gradual weakening of conviction.
At the height of psychosis, a patient may say:
“I am absolutely certain that someone is tracking me.”
Several weeks later, the same patient may acknowledge:
“It seemed completely real then, but I am less certain now.”
The underlying belief has not necessarily disappeared. However, certainty has given way to doubt.
This represents an important change in metacognitive functioning: the ability to reflect upon one’s own thoughts and consider alternative interpretations.
Clinically, attenuation may occur alongside reductions in anxiety, preoccupation and behaviours driven by the delusion.
The capacity to entertain uncertainty can be a meaningful therapeutic achievement.
Recovery may begin not when a person abandons a belief, but when the belief loses its absolute authority over their experience.
Fate 3: Encapsulation — The Delusion That Remains Isolated
Some patients continue to hold a delusional belief while functioning relatively well in other areas of life.
This phenomenon is traditionally described as encapsulation.
Consider a hypothetical patient who believes that a former neighbour deliberately interfered with their life several years ago.
The belief remains firmly held. However, it no longer dominates daily activities.
The patient works, maintains relationships, participates in family life and rarely discusses the belief unless directly questioned.
In this situation, the delusion has become relatively circumscribed.
Encapsulation is particularly relevant when assessing some chronic delusional states and residual psychotic symptoms.
It should not be confused with complete insight or remission of the belief itself.
A patient may function satisfactorily despite maintaining a highly unusual belief.
This illustrates why behavioural functioning and delusional conviction should be evaluated separately.
Fate 4: Transformation — A Belief Changes Its Form
Delusions sometimes evolve rather than disappear.
A broadly persecutory belief may become increasingly restricted to a specific person or event.
Alternatively, a previously elaborate delusional explanation may become a residual suspicion that is held with less certainty.
Some patients develop a more psychologically understandable interpretation of their previous experiences.
For example, a belief that strangers were deliberately communicating threatening messages may evolve into a general feeling of being unusually scrutinised or judged.
Clinicians sometimes describe an apparent shift from delusion to an overvalued idea.
However, this requires careful phenomenological assessment.
A delusion does not automatically become an overvalued idea simply because conviction decreases.
Overvalued ideas differ in their relationship to personal values, emotional investment, psychological understandability and reality testing.
They are not necessarily a final stage in the recovery of every delusion.
Fate 5: Persistence and Systematisation
Some delusions remain relatively stable or become increasingly elaborate.
New experiences may be incorporated into the existing belief system.
A patient convinced that others are conspiring against them may interpret ordinary disagreements, unexpected phone calls, or unrelated events as further confirmation.
Contradictory evidence may be discounted or reinterpreted.
Over time, multiple assumptions can become interconnected, creating a relatively coherent explanatory system.
Such persistence may be influenced by ongoing psychotic symptoms, cognitive processes, emotional distress, social isolation, avoidance behaviours and the personal meaning attached to the belief.
However, systematisation is not inevitable, and not every persistent delusion becomes elaborate.
Fate 6: Recurrence — The Return of a Familiar Delusional Theme
Perhaps the most interesting outcome is the reappearance of a previously resolved delusional theme during a later episode.
A patient may recover from a persecutory delusion and remain well for months or years.
During a subsequent episode, the same broad belief may return.
The specific details can change, but the central theme remains recognisable.
A 2024 longitudinal study published in JAMA Psychiatry examined delusional themes across episodes of psychosis.
Among 591 patients who initially experienced delusions, 558 achieved remission during follow-up in an early intervention service.
Of those who remitted, 182 subsequently relapsed. Among the 115 individuals who relapsed with threshold-level delusions, 104 (90.4%) experienced themes consistent with their initial episode.
This is a striking observation, although the 90.4% figure applies specifically to patients who relapsed with delusions—not to everyone who had experienced psychosis.
The finding suggests that delusional themes can remain remarkably consistent across episodes, even when the symptoms themselves remit between episodes.
It also has practical implications for recognising early warning signs of relapse.
3. Why Do Some Delusions Persist Despite Treatment?
The persistence of delusions has long challenged psychiatric theory.
Why should a belief remain convincing despite repeated experiences that appear to contradict it?
Several explanations have been proposed.
Aberrant Salience: When Ordinary Events Feel Extraordinary
Shitij Kapur’s influential aberrant-salience model provides one neurobiologically informed explanation.
Under ordinary circumstances, the brain assigns varying degrees of importance to internal and external events.
During psychosis, some relatively unimportant events may acquire exaggerated personal significance.
A passing glance, an advertisement, or a conversation between strangers may feel intensely meaningful.
A delusion may emerge as an explanation for these unusual experiences.
Within this model, antipsychotic treatment can reduce the abnormal significance attached to experiences.
The patient may initially feel less threatened or preoccupied even while continuing to believe the original explanation.
Only later might they begin reconsidering the belief itself.
This is a theoretical framework rather than a complete, experimentally established explanation for every delusion.
Belief Updating: Why Contradiction May Not Be Enough
The human brain continuously updates expectations using new information.
Bayesian accounts describe this process in terms of prior beliefs and the relative weight assigned to new evidence.
In psychosis, abnormalities in the weighting of prior expectations, sensory information or prediction errors may contribute to unusual beliefs.
Once a delusion becomes established, incoming information may be interpreted through the belief rather than used to revise it.
For example, someone who believes they are being monitored may interpret the absence of visible surveillance as evidence that the monitoring is sophisticated.
The explanation becomes increasingly difficult to disconfirm.
However, no single belief-updating abnormality adequately explains all delusions.
A 2026 systematic review by Lincoln and colleagues identified 74 theoretical accounts of delusion maintenance.
These included neurobiological, cognitive-behavioural, learning-based, motivational, social and Bayesian perspectives.
Their synthesis emphasised interacting mechanisms rather than a single cause.
Avoidance and Safety Behaviours
Persecutory delusions may also be sustained by avoidance.
A person who fears being harmed may avoid leaving home, talking to strangers or entering unfamiliar environments.
These behaviours can provide immediate relief from anxiety.
However, they may also prevent opportunities to discover that feared consequences do not occur.
The belief remains untested.
This mechanism is particularly relevant to psychological treatments that reduce avoidance and encourage carefully planned opportunities for corrective learning.
4. Can the Emotional Power of a Delusion Disappear Before the Belief Does?
Yes, and this is clinically significant.
A patient may continue to believe that a threatening event occurred but no longer experience overwhelming fear when discussing it.
Another may experience less preoccupation despite retaining substantial conviction.
These observations demonstrate that the emotional and cognitive components of delusions can change independently.
The Psychotic Symptom Rating Scales (PSYRATS) provide one framework for examining dimensions such as conviction, preoccupation, distress and disruption.
For example:
| Dimension | During acute psychosis | During improvement |
|---|---|---|
| Conviction | Complete certainty | Partial doubt or continued belief |
| Preoccupation | Dominates most of the day | Occasional thoughts |
| Emotional distress | Severe fear or agitation | Reduced distress |
| Behavioural impact | Avoidance and disruption | Improved participation in daily life |
| Insight | Limited awareness of illness | Variable improvement |
This is an illustrative pattern, not a mandatory clinical sequence.
It explains why a patient may demonstrate substantial functional recovery without achieving complete disappearance of delusional conviction.
The clinical goal is broader than changing the content of a belief.
It includes reducing suffering, restoring autonomy, improving functioning and preventing further episodes.
5. Delusions and Double Bookkeeping: Living in Two Realities
Classical European psychopathologists described an intriguing phenomenon known as double bookkeeping.
Some patients appear to maintain two relatively separate orientations towards reality.
For example, an individual may express a firm belief that they possess extraordinary powers while simultaneously managing ordinary financial responsibilities and following conventional social routines.
The extraordinary belief and everyday reality appear to coexist.
This phenomenon should not simply be interpreted as deliberate deception or evidence that the person does not genuinely hold the belief.
Contemporary phenomenological research suggests that some individuals experience a distinct delusional reality alongside the shared social world.
An empirical study published in 2023 found that this experience of dual reality could persist even during periods of symptomatic remission.
Double bookkeeping is therefore not identical to encapsulation or clinical recovery.
It is a phenomenological concept describing the coexistence of different orientations toward reality.
Understanding this helps clinicians avoid equating the absence of delusion-driven behaviour with the absence of delusional experience.
6. What Happens to the Memory of a Delusion After Recovery?
A delusion may disappear as a conviction while remaining as an autobiographical memory.
This distinction is important.
Imagine someone who previously believed they were being followed.
Following recovery, they may recognise that the experience was associated with illness.
Yet the memory of the fear remains vivid.
They may remember the sleepless nights, the feeling of danger, the embarrassment of their actions or the distress experienced by family members.
Thus, the delusion may no longer govern their interpretation of reality, but the emotional consequences of the episode remain significant.
This also explains why psychosis recovery sometimes involves psychological work beyond medication.
Patients may need opportunities to understand their experiences, repair relationships and rebuild confidence.
The paradox of recovering insight
Improving insight is generally desirable, but it can occasionally coincide with increased emotional distress.
As an individual recognises that previously unquestionable experiences occurred during psychosis, feelings of shame, regret, grief or fear about the future may emerge.
Post-psychotic depression is an important clinical concern, although not everyone experiences it.
The relationship between insight, depression and recovery is complex.
Clinicians should monitor mood and suicidal thoughts during recovery rather than assuming that improvement in psychotic symptoms guarantees psychological wellbeing.
A person can recover from a delusion while still needing help recovering from what the delusion meant to their life.
7. Can Psychotherapy Change the Fate of Delusions?
Psychological treatment increasingly recognises that delusions are more than isolated abnormalities of belief.
They are often accompanied by anxiety, threat anticipation, avoidance, sleep disturbance and changes in interpersonal relationships.
Cognitive behavioural therapy for psychosis (CBTp) may address these processes through collaborative exploration and appropriately structured behavioural experiments.
The objective is not to humiliate the patient or force acceptance of the clinician’s interpretation.
Instead, treatment may help the individual reconsider certainty, reduce avoidance and explore explanations that are less threatening.
The Feeling Safe Programme, developed by Daniel Freeman and colleagues, provides an example of targeted psychological treatment for persistent persecutory delusions.
In a randomised trial involving 130 participants, the programme achieved greater reductions in persecutory delusion conviction and severity than a befriending intervention.
A 2026 meta-analysis involving 904 participants across ten studies also found that CBT approaches produced small average improvements in persecutory delusion conviction and paranoia severity.
Psychotherapy therefore has an evidence-based role, although outcomes vary between individuals.
For many people with schizophrenia-spectrum disorders, psychological interventions are provided alongside appropriate medication and broader psychosocial care.
8. Does Medication Erase a Delusion?
Not in the way an eraser removes writing from a page.
Antipsychotic medications can reduce psychotic symptoms, including delusions, but their therapeutic effects emerge through complex pharmacological and psychological processes.
A reduction in abnormal salience, agitation or emotional distress may occur before a major change in conviction.
Some patients gradually reconsider previously fixed interpretations.
Others retain residual beliefs despite meaningful treatment response.
The response varies according to diagnosis, severity, duration of illness, adherence, coexisting conditions and individual factors.
Treatment should be reviewed systematically when significant symptoms persist.
For schizophrenia that has not responded adequately to appropriate antipsychotic trials, evidence-based guidelines recommend reassessing the diagnosis and treatment history and considering clozapine when criteria for treatment resistance are met.
Relapse prevention, physical health monitoring, psychological therapies and family support remain essential components of care.
9. How Should Clinicians Assess the Fate of a Delusion?
A single question such as “Do you still believe it?” provides only limited information.
Longitudinal assessment should examine several dimensions.
Belief: What does the patient currently believe? Has the content changed?
Conviction: How certain are they that the explanation is correct?
Preoccupation: How often does the belief occupy their attention?
Emotional response: Does it produce fear, anger, sadness or distress?
Behaviour: Does the belief affect decisions, relationships or daily functioning?
Insight: Can the patient consider alternative explanations?
Course: Does the belief fluctuate with stress, sleep disturbance, mood changes or psychotic relapse?
Standardised measures such as PSYRATS, alongside detailed clinical interviews, may help document these changes.
It is also useful to distinguish delusional remission from functional recovery and personal recovery.
A person may experience symptomatic improvement but continue to struggle with social withdrawal or occupational difficulties.
Conversely, someone with residual psychotic symptoms may successfully rebuild meaningful relationships and daily routines.
Both clinical and personal outcomes deserve attention.
10. What Is the Ultimate Fate of a Delusion?
There is no universal answer.
Some delusions disappear completely.
Others become less convincing, emotionally less significant or confined to a narrow area of experience.
Some remain persistent despite treatment.
Others return during later episodes, sometimes with remarkably similar themes.
The final outcome depends partly on the illness and its treatment, but also on psychological and social processes.
The clinician’s task is not merely to determine whether a delusion is present.
It is to understand how the experience is changing, how it affects the person, and what supports their recovery.
A reduction in conviction is meaningful.
A reduction in fear is meaningful.
Returning to work, reconnecting with family, and feeling safe in ordinary situations are also meaningful.
The disappearance of a delusion is one possible outcome. The restoration of a meaningful life is the broader goal of treatment.
Conclusion: From Certainty to Possibility
Delusions are often described as fixed beliefs, yet their clinical course reveals considerable dynamism.
They can emerge rapidly, consolidate into complex systems, soften with treatment, become encapsulated, or reappear during relapse.
Their emotional consequences may endure after the original conviction has disappeared.
For psychiatry, this suggests a more sophisticated understanding of recovery.
We should examine not only what a person believes, but also how strongly they believe it, how much suffering it causes, how it shapes their behaviour, and whether it continues to dominate their experience.
The fate of a delusion is ultimately a story about the changing relationship between belief, emotion, selfhood and reality.
And that story may continue long after the acute psychotic episode has ended.
About the Author
Dr. T. Srinivas Rajkumar, MBBS, MD (Psychiatry), DNB (Psychiatry)
Dr. Srinivas Rajkumar completed his medical education at Madurai Medical College and postgraduate training in Psychiatry at AIIMS, New Delhi.
He is a Consultant Psychiatrist practising in Chennai, with clinical interests in psychotic disorders, neuropsychiatry, psychopharmacology, psychological therapies and interventional psychiatry.
His clinical approach emphasises comprehensive psychiatric assessment, careful phenomenological understanding, evidence-based treatment and long-term functional recovery.
For individuals experiencing unusual beliefs, psychotic symptoms, relapse or difficulties recovering after an episode of psychosis, specialist psychiatric assessment can help establish the underlying diagnosis and develop an individualised treatment plan.
Appointments and consultations: www.srinivasaiims.com